In 2023, Tennessee passed a bill to restrict access of minors to “affirmative care”, though only minors who wanted blockers or hormones to assume the identity of his/her non-natal sex or to relieve gender dysphoria. Tennessee is now one of 15 states that has passed laws restricting affirmative care. Note, though, that hormones and blockers may, under that law, be used to treat other disorders (also called “differences”) of sex determination {DSDs).
Click title to read the bill. In it, “minor” refers to “an individual under 18 years of age”

From the bill:
The legislature determines that medical procedures that alter a minor’s hormonal balance, remove a minor’s sex organs, or otherwise change a minor’s physical appearance are harmful to a minor when these medical procedures are performed for the purpose of enabling a minor to identify with, or live as, a purported identity inconsistent with the minor’s sex or treating purported discomfort or distress from a discordance between the minor’s sex and asserted identity. These procedures can lead to the minor becoming irreversibly sterile, having increased risk of disease and illness, or suffering from adverse and sometimes fatal psychological consequences. Moreover, the legislature finds it likely that not all harmful effects associated with these types of medical procedures when performed on a minor are yet fully known, as many of these procedures, when performed on a minor for such purposes, are experimental in nature and not supported by high-quality, long-term medical studies.
The bill does not ban that aspect of “affirmative care” that involves psychological affirmation of a minor’s desires; what is banned is solely medical treatment given to minors. (I do think that good psychological treatment doesn’t have an aim at the outset, though, so “affirmative psychology” seems counterproductive).
But when you turn 18 in Tennessee, you can have all the hormones you want, though puberty blockers are by that point superfluous.
Yesterday, the U.S. Supreme Court upheld the law by a vote of 6-3—the ideological vote that we liberals are used to. There are long concurrences by Judges Alito (22 pages), Barrett (11 pages) and Thomas (23 pages), and dissents by Sotomayor (31 pages) and Kagan (2 pages). Click to see the decision:

And the end of the decision:

The Supreme Court decision reprised the Tennesse law:
In 2023, Tennessee joined the growing number of States restricting sex transition treatments for minors by enacting the Prohibition on Medical Procedures Performed on Minors Related to Sexual Identity, Senate Bill 1 (SB1). SB1 prohibits healthcare providers from prescribing, administering, or dispensing puberty blockers or hormones to any minor for the purpose of (1) enabling the minor to identify with, or live as, a purported identity inconsistent with the minor’s biological sex, or (2) treating purported discomfort or distress from a discordance between the minor’s biological sex and asserted identity. At the same time, SB1 permits a healthcare provider to administer puberty blockers or hormones to treat a minor’s congenital defect, precocious puberty, disease, or physical injury.
The National Law Review summarizes the decision and discusses its basis and what it did not address (click to read):

An excerpt:
In a 6-3 opinion authored by Chief Justice John Roberts, the Court in Skrmetti affirmed the U.S. Court of Appeals for the Sixth Circuit,[1] which held in September 2023 that (1) the Tennessee law does not discriminate on the basis of sex for purposes of equal protection, and (2) that it was subject only to rational basis review.
“SB1 does not classify on any bases that warrant heightened review,” the Supreme Court wrote. It concluded that the Tennessee law incorporates only two classifications: (1) age (allowing certain medical treatments for adults but not minors), and (2) medical use (allowing puberty blockers for minors for some conditions but not others). These two classifications warranted only rational basis review, the Court said.
And the Court dodged the question of whether transgender status should be considered a protected class equivalent to race or gender. “This case, in any event, does not raise that question because SB1 does not classify on transgender status.”
That’s a serious issue, for if transgender status is a protected class, the whole game changes. That doesn’t mean, though, that gender-dyphoric minors will immediately be allowed medical “affirmative care.” It goes on:
. . . The decision marks the first time the Supreme Court considered the application of the Equal Protection Clause to transgender youth, despite the decision skirting the question of whether transgender status should be considered a protected class.
The decision has broad implications, although many legal issues in this area remain unresolved.
Those unresolved issues are said to involve the right to privacy, parents’ rights, statutory discrimination analysis, impact of state constitutional arguments, and tension with state laws on gender identity. The upshot, it seems to me, is that the Court decided that the Tennessee law, because it didn’t discriminate on the basis of sex (both male and females with gender dysphoria are equally subject to Tennessee’s ban), was constitutional on those grounds. But that still leaves the issue of whether “transgender status” or “having gender dysphoria” counts as being a member of a protected class. If that proves to be the case in further legal wrangling, then affirmative medical care may be permitted.
I am not sure how this affects the 25 other states that do not have laws against medical affirmative care; those states have not passed bills banning it (or, presumably, allowing it) that can be adjudicated at the nation’s highest court. (I may be wrong here, so readers who know are welcome to correct me.)
Some of the mainstream media are couching this as a “setback for transgender rights”, but some of us would argue that there is not a “right” for minor who wishes to have surgery and/or hormone treatments aimed at making them resemble members of their non-natal sex should be able to freely get such treatments.
Here are two articles explicitly endorsing such a “right”:
From the Associated Press:


There was an NPR article called “Battle over rights of trans children is up at the Supreme Court,” but it has now changed the title (!). It does still assert the “rights” in one paragraph:
Front and center at the Supreme Court on Wednesday is the battle over the rights of transgender children. At issue is a state law in Tennessee that blocks minors from accessing gender-affirming care in the state.
I don’t want to scour all the news for similar statements, though, because I don’t believe there’s any “right” of minors to affirmative medical care beyond psychological treatment; there’s certainly no right in the Constitution or—in my view—ethics to have parts of your body cut off or hormones injected into you, particularly when the vast majority of minors experiencing gender dysphoria will resolve as being gay children who don’t need this kind of medical care (especially unproven blockers, who are banned for minors in some European countries).
Emily Yoffe, whose writings I’ve always found pretty sensible, agrees with me, and published the article below in the Free Press (archived here):


Some excerpts from Yoffe’s piece (bolding is mine):
The Court’s ruling is narrow; it says that a state has the right to regulate the practice. States, mostly blue, that still allow youth gender transition aren’t affected. But the decision will likely lend weight to the arguments of people who want to end the practice nationwide. And it will likely help the legal efforts by “detransitioners”—that is, young people who say they were pressured into life-altering treatments they now regret—to get compensation. Surely more such lawsuits will now be filed. Gender transition clinics will likely be under far more scrutiny: This Free Press story describes the cases of two such young women who were given prescriptions for testosterone after about a 30-minute appointment at Planned Parenthood.
Children who express gender distress often suffer from a host of other medical and psychological issues, such as autism, ADHD, depression, or anxiety, or have experienced various traumas. But to the gender doctors in their lucrative new clinics, there was only one answer to such childhood troubles: gender transition. This usually meant medically blocking a child’s normal puberty, then putting that patient on opposite-sex hormones: testosterone for girls, estrogen for boys. Sometimes complicated and painful surgeries were undertaken to try to create new genitals. Thousands of teenage girls, and some not even teenagers, have received double mastectomies, known euphemistically as “top surgery”—a surgical intervention normally reserved to treat breast cancer.
In the U.S., gender-distressed children and their parents were told that without the swift intervention of these radical treatments, the children were likely to commit suicide. It became a cliché for the reluctant parents of girls seeking to transition to be asked by the gender provider, “Would you rather have a live son or a dead daughter?” (And vice versa for parents of boys.)
The clinicians assured parents there was robust evidence underlying their interventions, but this was false. During the oral argument in the case, Chase Strangio, the lawyer for the ACLU, arguing to overturn Tennessee’s ban, was forced to acknowledge to Justice Samuel Alito that “completed suicide, thankfully and admittedly, is rare.”
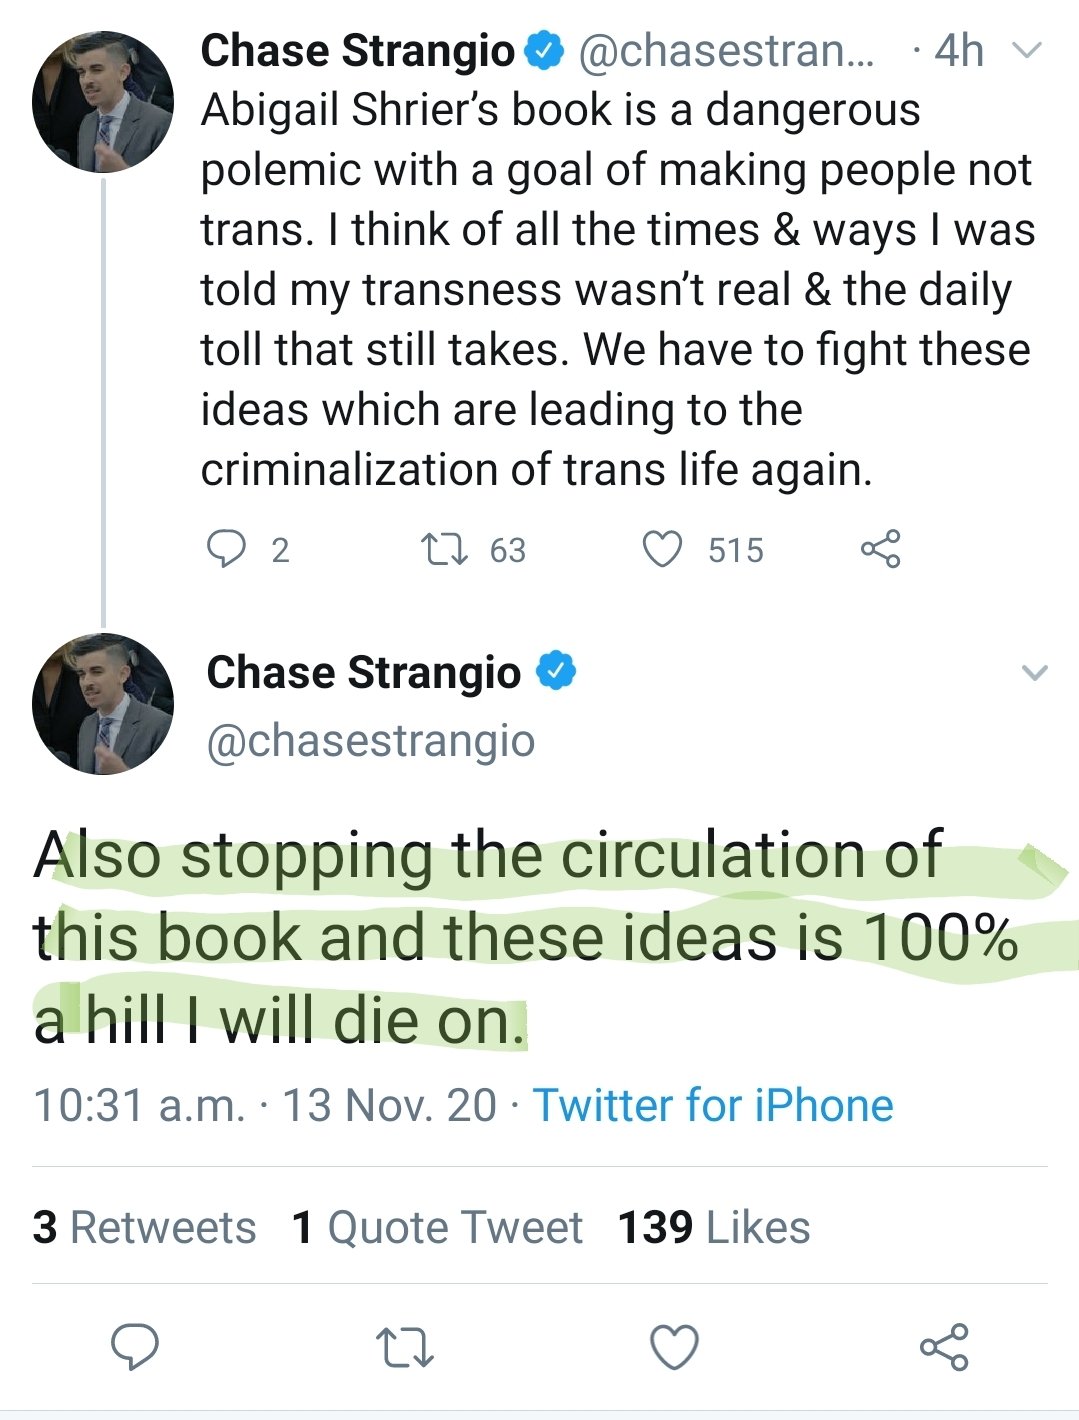
I would have guessed that Strangio would be in there argue for surgery and hormones; he was, after all, the ACLU lawyer who argued for banning Abigail Shrier’s book on rapid-onset gender dyphoria, often triggered by social pressure. (Strangio is also a trans-identified female.) In the end, Shrier was right. Shame on Strangio and the ACLU:

More from Yoffe:
. . . . The Court’s ruling notwithstanding, the U.S. medical establishment remains firmly behind the practice. Compare that to England, where a rigorous and independent report, the Cass Review, concluded that the evidence for pediatric transition is “remarkably weak.” Finland, Norway, and Sweden are among the other Western nations that have joined the UK in moving away from this treatment.
It is widely observed that the vast majority of young people with gender dysphoria—even those whose distress is “consistent, insistent, and persistent”—when allowed to go through normal puberty, come to accept their biological sex. (And there is no way to identify the very small number of children who will go on to experience lifelong gender distress.) Many of these children turn out to be gay, which is why a rising number of gay adults and gay-rights advocates have become alarmed that the transgender movement is medically transitioning gay kids. They argue that this movement has, intentionally or not, reified homophobic tropes.
I especially agree with the last paragraph below. In the future, I think medical gender-affirmative cafe will, along with our poor treatment of farm animals, be seen as practicers that were immoral in their time, but widely practiced:
Critics of the Supreme Court decision will argue that our major medical associations, from the American Academy of Pediatrics, to the American Medical Association, to the Endocrine Society, have all given support to this new branch of medicine. This is true. It is also true that these organizations or similar ones once supported lobotomies and eugenics. Just as that is a source of shame today, it is to be hoped that their vehement support of medically transitioning vulnerable young people will be a source of shame in the future. These medical societies have failed in their most basic duty of care to their patients by embracing a model that has so little evidence and such profound lifetime consequences.
When the history of this era is written, historians will have to explain how transgender activists so quickly took over institutions, and were able to so successfully threaten the social and work lives of those who objected. We are confident that historians will also remember those courageous individuals who, at the risk of professional and personal ruin, did so anyway.
But over at the Freedom From Religion Foundation, which now comprises a group of Chase Strangio clones, they’re proclaiming first that affirmative care is in general a salubrious way to address gender dysphoria, but also that affirmative care is “religious dogma.” That characterization is palpably ridiculous, meant as a way for the FFRF to pretend that its “progressive” politics are fully in line with its mission to keep church and state separate. But many atheists like me object to affirmative care. It is the FFRF’s deliberate conflation of progressive politics with church-state separation that I objected to, and this ultimately wound up with my resigning (along with Richard Dawkins and Steve Pinker) from the FFRF’s honorary board. Click below to read:

Note that the FFRF again speaks of transgender minors’ “rights”:
The Freedom From Religion Foundation lambastes today’s U.S. Supreme Court ruling upholding Tennessee’s cruel and unconstitutional ban on gender-affirming care for minors. This decision is a major blow to science-based medicine and the rights of parents and transgender youth.
, , , , Despite the hostile narrative surrounding transgender health care that the Supreme Court is furthering in its decision, the gender-affirming-care model is safe, effective and supported by every major medical organization, including the American Medical Association, the American Psychiatric Association, the American Psychological Association, the American Academy of Pediatrics and the American Academy of Child and Adolescent Psychiatry. These secular scientific organizations prioritize the safety and health of patients, not religious dogma.
The Freedom From Religion Foundation stands firmly with the transgender community, with parents, and with the medical professionals who follow science and ethics — not narrow sectarian belief — in providing care. FFRF will continue to educate about the harm these theocratic assaults are doing to civil liberties, bodily autonomy and the wall of separation between religion and government.
When the FFRF proclaims gender-affirming “model” as “safe, effective, and supported by every major medical association,” they of course neglect the fact that gender-affirming care is not seen that way in Europe, where it’s either banned or considered as experimental. And of course most gender-dysphoric minors who go through normal puberty don’t really need this care, as most turn out to be gay. No hormones or excising of body parts required. Affirmative treatment, as you may know, usually sterilizes its recipients, and, further, many of them will never have an orgasm after transitioning.
People like those in the FFRF are acting like this is the end of gender-affirmative care in America. I wish it were, and that treatment for dysphoria was limited to those over 18 (on same days I think 21). But in half of our states, hormones and surgery are still allowed, and there are no bans to be overturned. I think that such states are making a mistake treating youths who haven’t attained maturity as having the ability to make their full medical decisions, like catering to a minor who doesn’t like their left leg and wants it cut off. The “right” to make such decisions should not be given to minors, or even their parents or doctors—not until youths come of age.
This viewpoint may be seen as transphobic, but I firmly reject that adjective. After all, it’s not seen as transphobic in the UK, Sweden, Finland, or Denmark, which have severe restrictions on affirmative care. And in the future, those who defend this rush to cut and inject hormones will, I think, be seen as misguided or even barbaric.